Oral Juxtapid Helps Lower LDL-C, Playing an Important Role in the Management of HoFH1,2

The First and Only Oral Therapy Approved for HoFH in Patients 2+ Years1

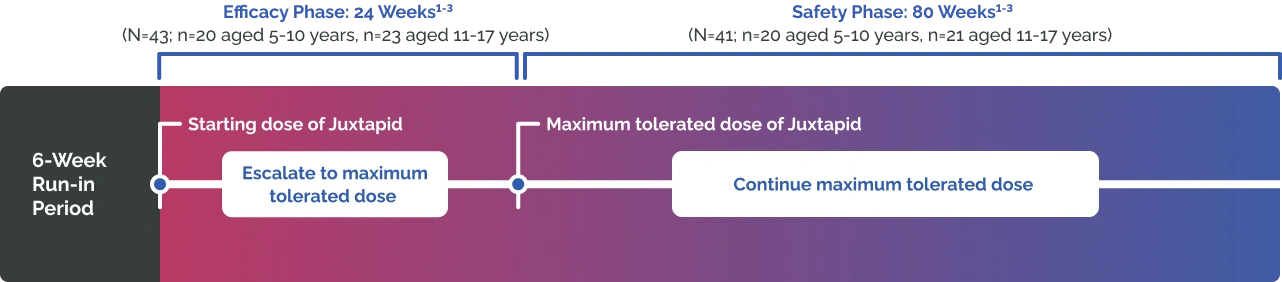
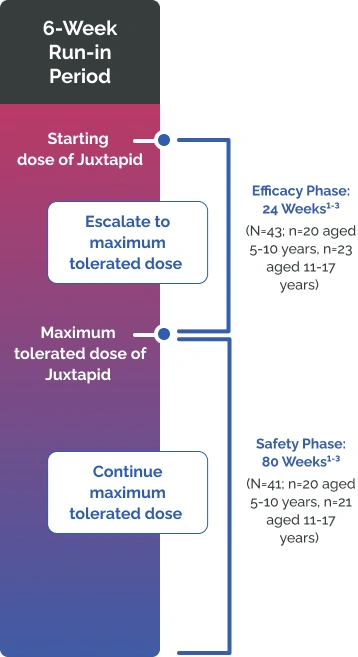
Juxtapid was evaluated in pediatric patients in a 104-week, open-label, single-arm, phase 3 clinical trial.2*

Forty-three pediatric patients with HoFH received Juxtapid and standard-of-care treatment.2

Timeline of Juxtapid clinical studies showing a 6-week run-in period followed by a core study of 78 weeks and a long-term extension study of 216 weeks. Key points include treatment start at week 0, primary endpoint at week 26, long-term safety endpoint at week 78, and primary endpoint at week 126. Timeline of Juxtapid clinical studies showing a 6-week run-in period followed by a core study of 78 weeks and a long-term extension study of 216 weeks. Key points include treatment start at week 0, primary endpoint at week 26, long-term safety endpoint at week 78, and primary endpoint at week 126.
logo-sign Concomitant lipid-lowering therapy included statins, ezetimibe, evolocumab, and lipoprotein apheresis (in 91%, 74%, 12%, and 44% of patients, respectively)2
logo-sign The primary study endpoint was the percentage reduction in LDL-C at week 242
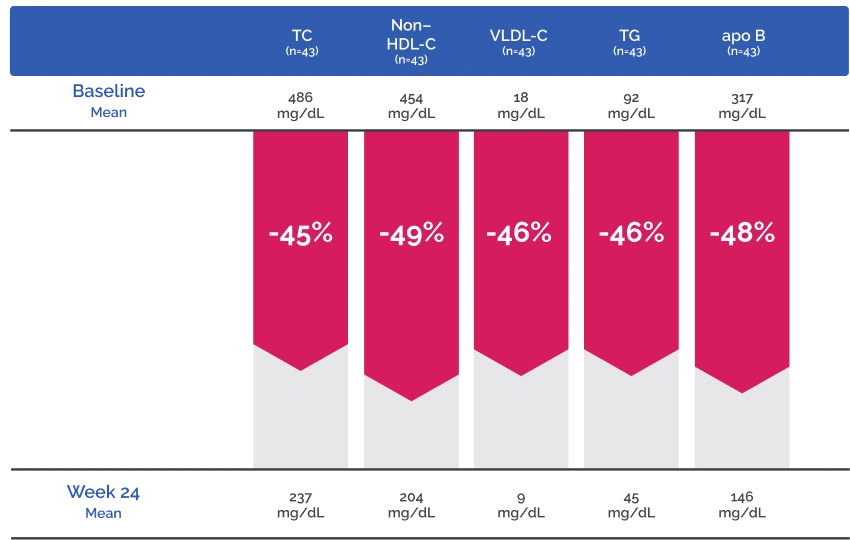
logo Secondary endpoint measures were the percentage change at week 24 in TC, non-HDL-C, VLDL-C, TG, and apo B2
logo An additional long-term analysis evaluated the safety and efficacy of Juxtapid up to week 1044
*Efficacy data vary between the Juxtapid Prescribing Information and the Masana et al article as a result of differing statistical methodology between the authors of the study and the US Food and Drug Administration.

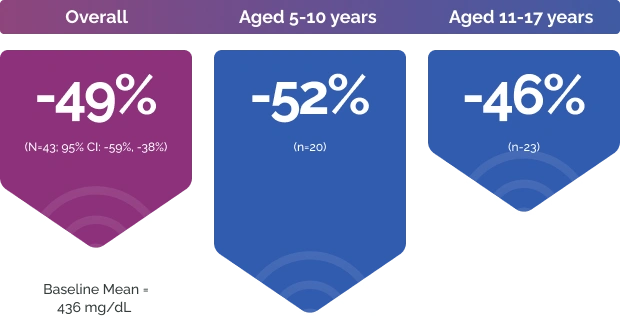
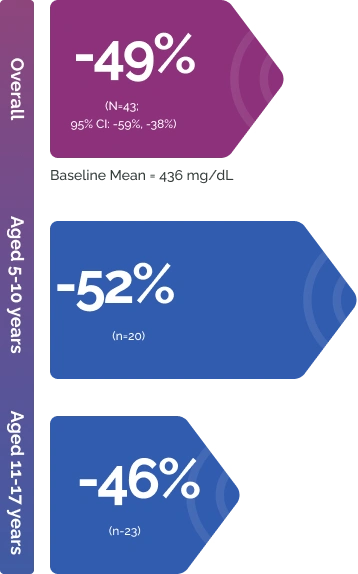
Reductions in LDL-C Among Pediatric Patients1

LDL-C reductions of 46% were observed in patients aged 11-17 years and 52% in patients aged 5-10 years.1
logo-sign
LDL-C reductions were achieved in patients already receiving maximally tolerated statin and/or ezetimibe therapy, with widespread use of apheresis (44% of patients at baseline).2
Mean percentage change in LDL-C from baseline1
LDL-C reductions with Juxtapid: 40% in intent-to-treat population at week 26, 50% in patients completing treatment per protocol at week 26, and 45.5% in patients enrolled in the long-term extension at week 126. LDL-C reductions with Juxtapid: 40% in intent-to-treat population at week 26, 50% in patients completing treatment per protocol at week 26, and 45.5% in patients enrolled in the long-term extension at week 126.

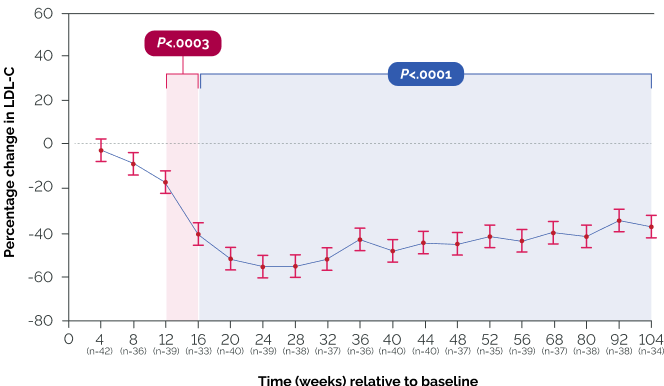
Meaningful and Persistent LDL-C Reductions

Reductions at any time through week 242:
42%
Patients who reached
LDL-C target of <135 mg/dL
(n=18)
37%
Patients who reached
LDL-C target of <115 mg/dL
(n=16)
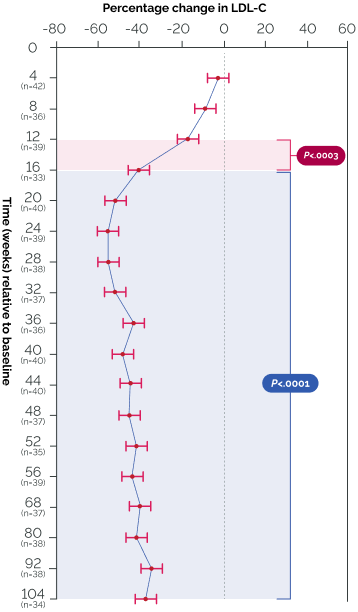
Mean percentage change in LDL-C vs baseline4
Right ImageRight Mobile Image
Icon Left
Reductions were maintained during long-term treatment (over 2 years) particularly in patients not receiving LDL apheresis at baseline.4

Broad Improvement Observed Across Lipid Parameters2

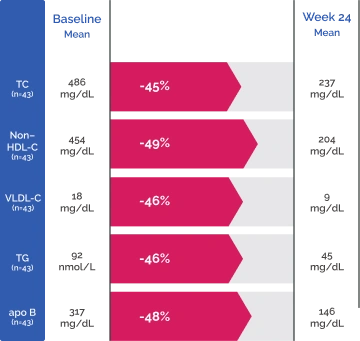
Participants saw reductions in other key secondary endpoints: TC, non–HDL-C, VLDL-C, TG, and apo B.2

logo
TC, TG, apo B, non-HDL-C, and VLDL-C are known to be important indicators of atherosclerotic cardiovascular disease risk in patients with familial hypercholesterolemia.2
Mean percentage change in lipids and lipoproteins vs baseline1
/_assets/images/v3/lipids/ldl-baseline-chart-pediatric-mobile.webp/_assets/images/v3/lipids/ldl-baseline-chart-pediatric-mobile.webp
References:
1. JUXTAPID (lomitapide) Prescribing Information. Chiesi Farmaceutici S.p.A.; 2026. 2. Masana L, Zambon A, Schmitt CP, et al. Lomitapide for the treatment of paediatric patients with homozygous familial hypercholesterolaemia (APH-19): results from the efficacy phase of an open-label, multicentre, phase 3 study. Lancet Diabetes Endocrinol. 2024;12(12):880-889. doi:10.1016/S2213-8587(24)00233-X 3. Supplement to: Masana L, Zambon A, Schmitt CP, et al. Lomitapide for the treatment of paediatric patients with homozygous familial hypercholesterolaemia (APH-19): results from the efficacy phase of an open-label, multicentre, phase 3 study. Lancet Diabetes Endocrinol. 2024;12(12):880-889. doi:10.1016/S2213-8587(24)00233-X 4. Masana-Marín L, Zambon A, Schmitt CP, et al. Lomitapide in paediatric patients with homozygous familial hypercholesterolaemia (HOFH)—analysis of long-term (104-week) safety and efficacy from the APH-19 study [abstract]. Atherosclerosis. 2025;407(suppl):120361.

INDICATION AND IMPORTANT SAFETY INFORMATION

INDICATION

JUXTAPID (lomitapide) is a microsomal triglyceride transfer protein inhibitor indicated as an adjunct to a low-fat diet and exercise and other low-density lipoprotein cholesterol (LDL-C) therapies, to reduce LDL-C in adult and pediatric patients aged 2 years and older with homozygous familial hypercholesterolemia (HoFH).

IMPORTANT SAFETY INFORMATION

WARNING: RISK OF HEPATOTOXICITY

JUXTAPID can cause elevations in transaminases. In the adult clinical trial, 10 (34%) of the 29 patients treated with JUXTAPID had at least one elevation in alanine aminotransferase (ALT) or aspartate aminotransferase (AST) ≥3 times the upper limit of normal (ULN). There were no concomitant clinically meaningful elevations of total bilirubin, international normalized ratio (INR), or alkaline phosphatase. In the pediatric clinical trial (5 to 17 years of age), 6 (14%) of the 43 patients experienced elevations in ALT and/or AST ≥ 3 times ULN. No concomitant clinically meaningful elevations in total bilirubin or alkaline phosphatase were observed.

JUXTAPID also increases hepatic fat, with or without concomitant increases in transaminases. The median absolute increase in hepatic fat in adult patients was 6% after both 26 and 78 weeks of treatment, from 1% at baseline, measured by magnetic resonance spectroscopy (MRS). The median absolute increase in hepatic fat in pediatric patients aged 5 to 17 years was 4% after 24 weeks and 104 weeks of treatment, from 3% at baseline, measured by nuclear magnetic resonance (NMR). Hepatic steatosis associated with JUXTAPID treatment may be a risk factor for progressive liver disease, including steatohepatitis and cirrhosis.

Measure ALT, AST, alkaline phosphatase, and total bilirubin before initiating treatment and then ALT and AST regularly as recommended. During treatment, adjust the dose of JUXTAPID if the ALT or AST are ≥3 times ULN. Discontinue JUXTAPID for clinically significant liver toxicity.

Because of the risk of hepatotoxicity, JUXTAPID is available only through a restricted program under a Risk Evaluation and Mitigation Strategy (REMS) called the JUXTAPID REMS Program. Prescribe JUXTAPID only to patients with a clinical or laboratory diagnosis consistent with HoFH. The safety and effectiveness of JUXTAPID have not been established in patients with hypercholesterolemia who do not have HoFH.

CONTRAINDICATIONS

  • Pregnancy
  • Concomitant use with strong or moderate CYP3A4 inhibitors
  • Moderate or severe hepatic impairment or active liver disease including unexplained persistent abnormal liver function tests

WARNINGS AND PRECAUTIONS

Risk of Hepatotoxicity

JUXTAPID can cause elevations in transaminases and hepatic steatosis in adult and pediatric patients. JUXTAPID may induce steatohepatitis, which can progress to cirrhosis over several years.

Elevations in transaminases (ALT and/or AST) are associated with JUXTAPID. Before initiating JUXTAPID and during treatment, monitor transaminases as recommended below:

  • Before initiating treatment, measure ALT, AST, alkaline phosphatase, and total bilirubin. If abnormal, consider initiating JUXTAPID only after an appropriate work-up and the baseline abnormalities have been explained or resolved.
  • During the first year of treatment, measure liver-related tests (ALT and AST, at a minimum) prior to each increase in dose or monthly, whichever occurs first.
  • After the first year of treatment, measure liver-related tests (ALT and AST, at a minimum) at least every 3 months and before any increase in dose.
  • At any time during the treatment, if transaminases are >1 and <3 times ULN, no dose modification is required. Continue routine monitoring of liver-related tests (once monthly during the first year of treatment and every 3 months thereafter). If transaminases are ≥3 times ULN, reduce or withhold dosing of JUXTAPID and monitor as recommended. Discontinue JUXTAPID for persistent or clinically significant elevations. If transaminase elevations are accompanied by clinical symptoms of liver injury (such as nausea, vomiting, abdominal pain, fever, jaundice, lethargy, flu-like symptoms), increases in bilirubin ≥2 times ULN, or active liver disease, discontinue treatment with JUXTAPID and identify the probable cause.

JUXTAPID increases hepatic fat, with or without concomitant increases in transaminases. Hepatic steatosis is a risk factor for progressive liver disease, including steatohepatitis and cirrhosis. The long-term consequences of hepatic steatosis associated with JUXTAPID treatment are unknown.

Alcohol may increase levels of hepatic fat and induce or exacerbate liver injury. Drinking more than one alcoholic drink per day is not recommended for patients taking JUXTAPID.

Exercise caution when using JUXTAPID with other medications known to have potential for hepatotoxicity, such as isotretinoin, amiodarone, acetaminophen (>4 g/day for ≥3 days/week), methotrexate, tetracyclines, and tamoxifen.

JUXTAPID REMS Program

Because of the risk of hepatotoxicity associated with JUXTAPID therapy, JUXTAPID is available through a restricted program under the REMS. Under the JUXTAPID REMS, only certified healthcare providers and pharmacies may prescribe and distribute JUXTAPID. Further information is available at www.JUXTAPIDREMSProgram.com or by telephone at 1-85-JUXTAPID (1-855-898-2743).

Embryo-Fetal Toxicity

Based on findings from animal studies, JUXTAPID use is contraindicated in pregnancy since it may cause fetal harm. Females of reproductive potential should have a negative pregnancy test before starting JUXTAPID. Advise females of reproductive potential to use effective contraception during therapy with JUXTAPID and for two weeks after the final dose. If pregnancy is detected, discontinue JUXTAPID.

Reduced Absorption of Fat-Soluble Vitamins and Serum Fatty Acids

Given its mechanism of action in the small intestine, JUXTAPID may reduce the absorption of fat-soluble nutrients. Patients treated with JUXTAPID should take daily nutritional supplements that contain the recommended dosages of vitamin E and essential fatty acids. Patients with chronic bowel or pancreatic diseases that predispose to malabsorption may be at increased risk for deficiencies in these nutrients with use of JUXTAPID.

Gastrointestinal Adverse Reactions

Gastrointestinal adverse reactions are common and may lead to treatment discontinuation. Instruct patients to stop JUXTAPID and contact their healthcare provider if severe diarrhea occurs or if they experience symptoms of volume depletion, such as lightheadedness, decreased urine output, or tiredness. In such cases, consider reducing the dose or suspending use of JUXTAPID. To reduce the risk of gastrointestinal adverse reactions, instruct patients or their caregiver(s) to adhere to a low-fat diet supplying <20% of energy from fat or less than 30 grams of fat, whichever is less. Increase the dosage of JUXTAPID gradually. Individualize the maximum daily fat goal based on caloric needs due to age, growth, activity level, and tolerability. Monitor growth and weight loss in pediatric patients who are below the 10th percentile for height, weight, or BMI.

Concomitant Use of CYP3A4 Inhibitors

CYP3A4 inhibitors increase the exposure of lomitapide, with strong inhibitors increasing exposure approximately 27-fold. Concomitant use of moderate or strong CYP3A4 inhibitors with JUXTAPID is contraindicated. Weak CYP3A4 inhibitors can increase the exposure of lomitapide approximately 2-fold; therefore, when JUXTAPID is administered with weak CYP3A4 inhibitors, the dose of JUXTAPID should be decreased by half.

Risk of Myopathy with Concomitant Use of Simvastatin or Lovastatin

The risk of myopathy, including rhabdomyolysis, with simvastatin and lovastatin monotherapy is dose related. Lomitapide approximately doubles the exposure to simvastatin; therefore, it is recommended to reduce the dose of simvastatin by 50% when initiating JUXTAPID. Reducing the dose of lovastatin should be considered when initiating JUXTAPID.

Risk of Supratherapeutic or Subtherapeutic Anticoagulation with Warfarin

JUXTAPID increases the plasma concentrations of warfarin. Increases or decreases in the dose of JUXTAPID may lead to supra- or subtherapeutic anticoagulation, respectively. Patients taking warfarin should undergo regular monitoring of the INR, especially after any changes in JUXTAPID dosage. The dose of warfarin should be adjusted as clinically indicated.

Risk of Malabsorption with Rare Hereditary Disorders of Galactose Intolerance

Patients with rare, hereditary problems of galactose intolerance, the Lapp lactase deficiency, or glucose-galactose malabsorption should avoid JUXTAPID.

ADVERSE REACTIONS

The most common adverse reactions in adult patients (incidence ≥10%) are diarrhea, nausea, dyspepsia, vomiting, and abdominal pain.

The most common adverse reactions in pediatric patients aged 5 to 17 years old (incidence ≥15%) are abdominal pain, alanine aminotransferase increased, aspartate aminotransferase increased, diarrhea, and vomiting.

REPORTING OF ADVERSE REACTIONS

All healthcare professionals should report all suspected adverse reactions. Please contact Chiesi Farmaceutici S.p.A. at 1-888-661-9260 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.

USE IN SPECIFIC POPULATIONS

Because of the potential for serious adverse reactions, including hepatotoxicity, advise patients that breastfeeding is not recommended during treatment with JUXTAPID. Advise females of reproductive potential to use effective contraception during treatment with JUXTAPID and for two weeks after the final dose. In patients with end-stage renal disease (eGFR <15 mL/min/1.73 m2) receiving hemodialysis, lomitapide exposure increased approximately 50% compared with healthy volunteers. The maximum recommended dosage of JUXTAPID in patients with end-stage renal disease receiving hemodialysis is lower than in those with normal renal function.

Please see Full Prescribing Information, including BOXED WARNING, and the Medication Guide.

<

INDICATION AND IMPORTANT SAFETY INFORMATION

INDICATION

JUXTAPID (lomitapide) is a microsomal triglyceride transfer protein inhibitor indicated as an adjunct to a low-fat diet and exercise and other low-density lipoprotein cholesterol (LDL-C) therapies, to reduce LDL-C in adult and pediatric patients aged 2 years and older with homozygous familial hypercholesterolemia (HoFH).

IMPORTANT SAFETY INFORMATION

WARNING: RISK OF HEPATOTOXICITY

JUXTAPID can cause elevations in transaminases. In the adult clinical trial, 10 (34%) of the 29 patients treated with JUXTAPID had at least one elevation in alanine aminotransferase (ALT) or aspartate aminotransferase (AST) ≥3 times the upper limit of normal (ULN). There were no concomitant clinically meaningful elevations of total bilirubin, international normalized ratio (INR), or alkaline phosphatase. In the pediatric clinical trial (5 to 17 years of age), 6 (14%) of the 43 patients experienced elevations in ALT and/or AST ≥ 3 times ULN. No concomitant clinically meaningful elevations in total bilirubin or alkaline phosphatase were observed.

JUXTAPID also increases hepatic fat, with or without concomitant increases in transaminases. The median absolute increase in hepatic fat in adult patients was 6% after both 26 and 78 weeks of treatment, from 1% at baseline, measured by magnetic resonance spectroscopy (MRS). The median absolute increase in hepatic fat in pediatric patients aged 5 to 17 years was 4% after 24 weeks and 104 weeks of treatment, from 3% at baseline, measured by nuclear magnetic resonance (NMR). Hepatic steatosis associated with JUXTAPID treatment may be a risk factor for progressive liver disease, including steatohepatitis and cirrhosis.

Measure ALT, AST, alkaline phosphatase, and total bilirubin before initiating treatment and then ALT and AST regularly as recommended. During treatment, adjust the dose of JUXTAPID if the ALT or AST are ≥3 times ULN. Discontinue JUXTAPID for clinically significant liver toxicity.

Because of the risk of hepatotoxicity, JUXTAPID is available only through a restricted program under a Risk Evaluation and Mitigation Strategy (REMS) called the JUXTAPID REMS Program. Prescribe JUXTAPID only to patients with a clinical or laboratory diagnosis consistent with HoFH. The safety and effectiveness of JUXTAPID have not been established in patients with hypercholesterolemia who do not have HoFH.

CONTRAINDICATIONS

WARNINGS AND PRECAUTIONS

Risk of Hepatotoxicity

JUXTAPID can cause elevations in transaminases and hepatic steatosis in adult and pediatric patients. JUXTAPID may induce steatohepatitis, which can progress to cirrhosis over several years.

Elevations in transaminases (ALT and/or AST) are associated with JUXTAPID. Before initiating JUXTAPID and during treatment, monitor transaminases as recommended below:

JUXTAPID increases hepatic fat, with or without concomitant increases in transaminases. Hepatic steatosis is a risk factor for progressive liver disease, including steatohepatitis and cirrhosis. The long-term consequences of hepatic steatosis associated with JUXTAPID treatment are unknown.

Alcohol may increase levels of hepatic fat and induce or exacerbate liver injury. Drinking more than one alcoholic drink per day is not recommended for patients taking JUXTAPID.

Exercise caution when using JUXTAPID with other medications known to have potential for hepatotoxicity, such as isotretinoin, amiodarone, acetaminophen (>4 g/day for ≥3 days/week), methotrexate, tetracyclines, and tamoxifen.

JUXTAPID REMS Program

Because of the risk of hepatotoxicity associated with JUXTAPID therapy, JUXTAPID is available through a restricted program under the REMS. Under the JUXTAPID REMS, only certified healthcare providers and pharmacies may prescribe and distribute JUXTAPID. Further information is available at www.JUXTAPIDREMSProgram.com or by telephone at 1-85-JUXTAPID (1-855-898-2743).

Embryo-Fetal Toxicity

Based on findings from animal studies, JUXTAPID use is contraindicated in pregnancy since it may cause fetal harm. Females of reproductive potential should have a negative pregnancy test before starting JUXTAPID. Advise females of reproductive potential to use effective contraception during therapy with JUXTAPID and for two weeks after the final dose. If pregnancy is detected, discontinue JUXTAPID.

Reduced Absorption of Fat-Soluble Vitamins and Serum Fatty Acids

Given its mechanism of action in the small intestine, JUXTAPID may reduce the absorption of fat-soluble nutrients. Patients treated with JUXTAPID should take daily nutritional supplements that contain the recommended dosages of vitamin E and essential fatty acids. Patients with chronic bowel or pancreatic diseases that predispose to malabsorption may be at increased risk for deficiencies in these nutrients with use of JUXTAPID.

Gastrointestinal Adverse Reactions

Gastrointestinal adverse reactions are common and may lead to treatment discontinuation. Instruct patients to stop JUXTAPID and contact their healthcare provider if severe diarrhea occurs or if they experience symptoms of volume depletion, such as lightheadedness, decreased urine output, or tiredness. In such cases, consider reducing the dose or suspending use of JUXTAPID. To reduce the risk of gastrointestinal adverse reactions, instruct patients or their caregiver(s) to adhere to a low-fat diet supplying <20% of energy from fat or less than 30 grams of fat, whichever is less. Increase the dosage of JUXTAPID gradually. Individualize the maximum daily fat goal based on caloric needs due to age, growth, activity level, and tolerability. Monitor growth and weight loss in pediatric patients who are below the 10th percentile for height, weight, or BMI.

Concomitant Use of CYP3A4 Inhibitors

CYP3A4 inhibitors increase the exposure of lomitapide, with strong inhibitors increasing exposure approximately 27-fold. Concomitant use of moderate or strong CYP3A4 inhibitors with JUXTAPID is contraindicated. Weak CYP3A4 inhibitors can increase the exposure of lomitapide approximately 2-fold; therefore, when JUXTAPID is administered with weak CYP3A4 inhibitors, the dose of JUXTAPID should be decreased by half.

Risk of Myopathy with Concomitant Use of Simvastatin or Lovastatin

The risk of myopathy, including rhabdomyolysis, with simvastatin and lovastatin monotherapy is dose related. Lomitapide approximately doubles the exposure to simvastatin; therefore, it is recommended to reduce the dose of simvastatin by 50% when initiating JUXTAPID. Reducing the dose of lovastatin should be considered when initiating JUXTAPID.

Risk of Supratherapeutic or Subtherapeutic Anticoagulation with Warfarin

JUXTAPID increases the plasma concentrations of warfarin. Increases or decreases in the dose of JUXTAPID may lead to supra- or subtherapeutic anticoagulation, respectively. Patients taking warfarin should undergo regular monitoring of the INR, especially after any changes in JUXTAPID dosage. The dose of warfarin should be adjusted as clinically indicated.

Risk of Malabsorption with Rare Hereditary Disorders of Galactose Intolerance

Patients with rare, hereditary problems of galactose intolerance, the Lapp lactase deficiency, or glucose-galactose malabsorption should avoid JUXTAPID.

ADVERSE REACTIONS

The most common adverse reactions in adult patients (incidence ≥10%) are diarrhea, nausea, dyspepsia, vomiting, and abdominal pain.

The most common adverse reactions in pediatric patients aged 5 to 17 years old (incidence ≥15%) are abdominal pain, alanine aminotransferase increased, aspartate aminotransferase increased, diarrhea, and vomiting.

REPORTING OF ADVERSE REACTIONS

All healthcare professionals should report all suspected adverse reactions. Please contact Chiesi Farmaceutici S.p.A. at 1-888-661-9260 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.

USE IN SPECIFIC POPULATIONS

Because of the potential for serious adverse reactions, including hepatotoxicity, advise patients that breastfeeding is not recommended during treatment with JUXTAPID. Advise females of reproductive potential to use effective contraception during treatment with JUXTAPID and for two weeks after the final dose. In patients with end-stage renal disease (eGFR <15 mL/min/1.73 m2) receiving hemodialysis, lomitapide exposure increased approximately 50% compared with healthy volunteers. The maximum recommended dosage of JUXTAPID in patients with end-stage renal disease receiving hemodialysis is lower than in those with normal renal function.

Please see Full Prescribing Information, including BOXED WARNING, and the Medication Guide.

<
PP-RA-02053 V1.0